| Treatment | Surgery for Frozen Pelvis |
|---|---|
| Used for | Severe pelvic adhesions associated with conditions such as advanced endometriosis, previous pelvic surgery, infection or inflammation |
| How it works | Adhesions are carefully divided to separate pelvic organs, restore anatomy where possible and treat the underlying condition |
| Anaesthesia | General anaesthesia |
| Surgical approach | Laparoscopic, robotic-assisted or open surgery, depending on the extent and complexity of adhesions |
| Hospital stay | Varies according to the complexity of surgery, organs involved and individual recovery |
| Downtime | Usually several weeks, although recovery varies considerably according to the extent of surgery |
| Treatment course | Usually performed as a single surgical procedure with post-operative follow-up |
| Suitable for | Women with severe pelvic adhesions causing significant symptoms, organ involvement or other complications where surgical treatment is appropriate |
A frozen pelvis describes a severe form of pelvic adhesive disease in which dense bands of scar tissue, known as adhesions, cause pelvic organs and tissues to become abnormally attached to one another. The uterus, ovaries, fallopian tubes, bowel, bladder and surrounding pelvic structures may become fixed in place, resulting in significant distortion of the normal pelvic anatomy.
A frozen pelvis is not a disease in itself, but a description of extensive scarring and adhesions that can develop as a result of an underlying condition. Endometriosis is an important cause, particularly when disease is severe, although previous surgery, infection and other inflammatory processes can also lead to extensive pelvic adhesions.
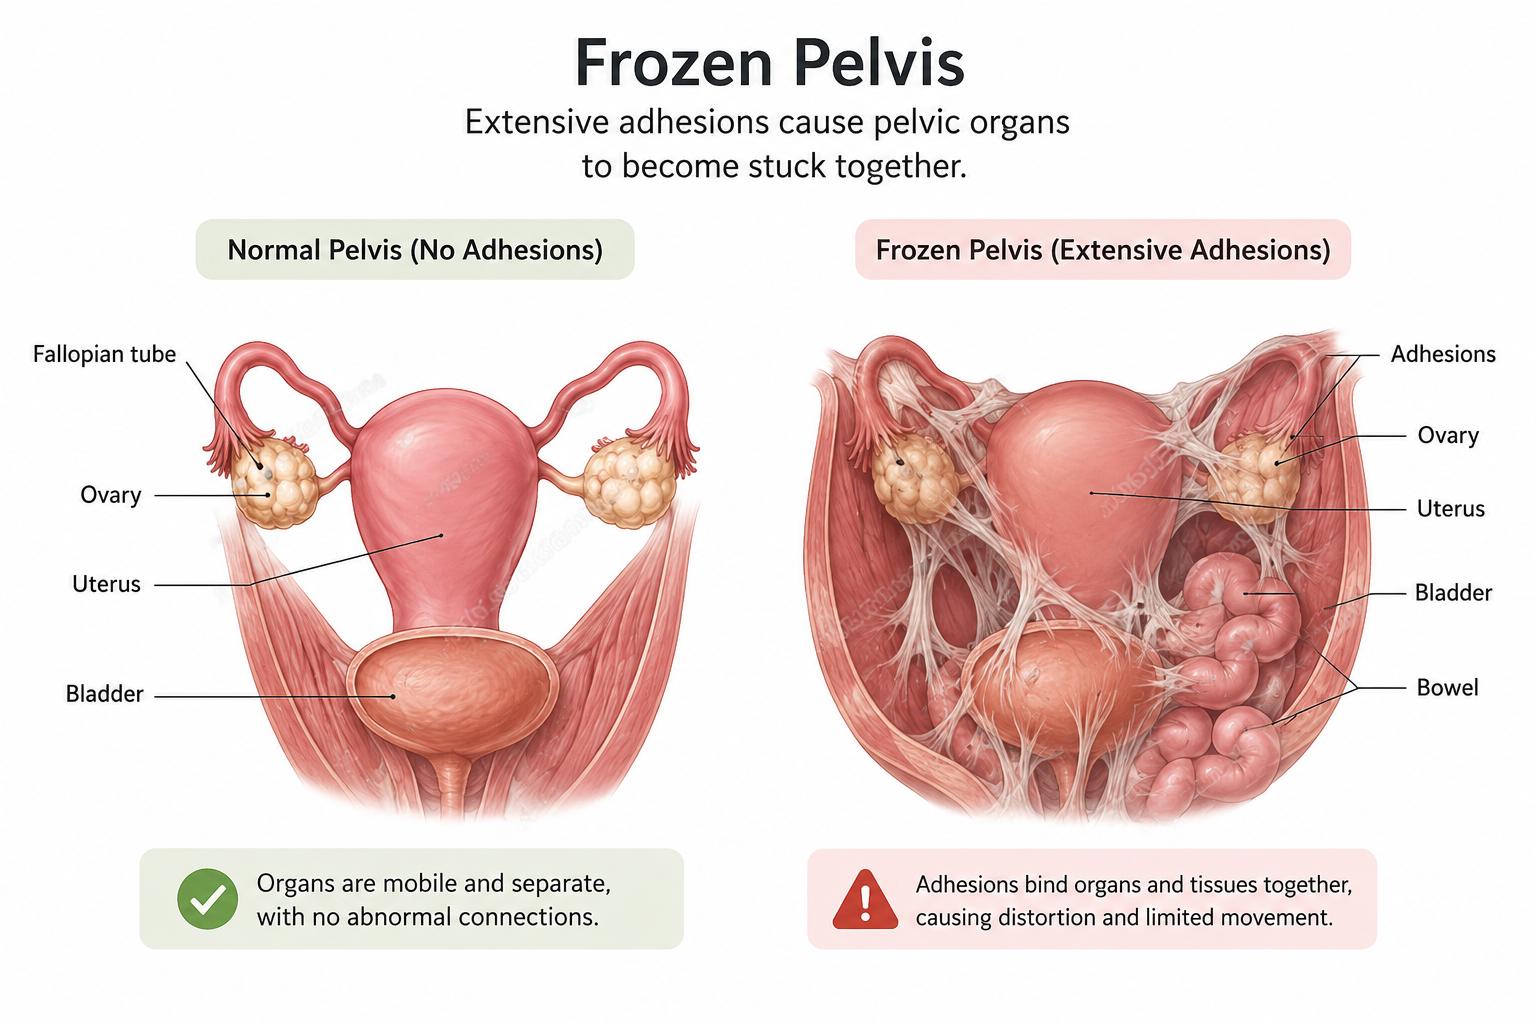
A frozen pelvis develops when extensive inflammation, tissue damage and subsequent healing lead to dense adhesions within the pelvis. Possible causes include:
Symptoms depend on the underlying cause, severity of the adhesions and which pelvic organs are affected. Some women may experience:
The presence of adhesions does not always correspond with the severity of symptoms, and some pelvic adhesions may cause few or no noticeable symptoms.

Assessment usually begins with a detailed medical and gynaecological history, including symptoms, previous pelvic or abdominal operations, infections and conditions such as endometriosis. A pelvic examination may help identify reduced mobility, tenderness or other findings that suggest significant pelvic disease.
Pelvic ultrasound is commonly used to assess the uterus, ovaries and surrounding structures, while MRI may provide additional information when deep endometriosis or complex pelvic disease is suspected. Imaging can help with surgical planning, but it may not show every adhesion. In some cases, the full extent of pelvic adhesions and anatomical distortion only becomes apparent during surgery.
Not every patient with pelvic adhesions requires surgery. Surgical treatment may be considered when symptoms are significant, complications develop or an underlying condition requires operative treatment. This may include women with:
The decision to operate requires careful assessment because surgery for a frozen pelvis can be complex, particularly when multiple organs are involved.
Surgery aims to carefully separate structures affected by adhesions and treat the underlying condition where appropriate. The surgical approach depends on the severity of adhesions, organs involved and complexity of the planned procedure.
The appropriate approach is selected according to the underlying condition, extent of adhesions, organs involved, previous operations and any additional procedures required.
Frozen pelvis surgery is performed under general anaesthesia. The exact procedure varies considerably because the location and severity of adhesions and the organs involved differ between patients.
| Stage | What Happens |
|---|---|
| Pre-operative Preparation | Your medical history, imaging, previous operations and medications are reviewed, and you receive instructions for preparing for surgery. |
| General Anaesthesia | Anaesthesia is administered so that you remain unconscious throughout the operation. |
| Surgical Access | The pelvis is accessed using the planned laparoscopic, robotic-assisted or open surgical approach. |
| Assessment of Adhesions | The surgeon assesses the extent of adhesions, anatomical distortion and involvement of surrounding pelvic organs. |
| Adhesiolysis | Dense adhesions are carefully divided to separate organs and tissues that have become abnormally attached. |
| Treatment of Underlying Disease | Conditions contributing to the frozen pelvis, such as endometriosis, may be surgically treated where appropriate. |
| Treatment of Affected Organs | Additional procedures may be required if structures such as the ovaries, bowel, bladder or ureters are significantly affected. |
| Completion and Recovery | Once the planned surgery is completed, the surgical sites are closed and you are monitored while recovering from anaesthesia. |
Adhesiolysis is a surgical procedure used to divide adhesions, which are bands of scar tissue that cause organs or tissues to become abnormally attached. During frozen pelvis surgery, adhesiolysis is performed carefully to separate affected pelvic structures and restore their normal anatomy and mobility as far as safely possible.
The extent of adhesiolysis depends on the severity and location of the adhesions and the organs involved. Although existing adhesions can be divided, surgery cannot guarantee that they will not reform because new adhesions can develop as tissues heal after an operation.
A frozen pelvis can involve several reproductive, urinary and digestive structures, particularly when adhesions are extensive. Structures that may be affected include:
When extensive adhesions involve the bowel, bladder or urinary tract, surgery may require additional planning and, in selected complex cases, involvement of other surgical specialists.
Surgery aims to release severe adhesions, treat the underlying pelvic condition where appropriate and address problems caused by distorted pelvic anatomy. Potential benefits for appropriately selected patients include:
Outcomes depend on the underlying condition, severity of adhesions and organs involved. Surgery cannot guarantee complete symptom relief or prevent adhesions from forming again.
Surgery may be considered when severe pelvic adhesions cause significant symptoms, complications or interfere with the treatment of an underlying condition. It may be appropriate for women with:
Frozen pelvis surgery can be complex, particularly when dense adhesions involve several pelvic organs. Treatment planning should therefore consider the extent of surgery that may be required and its potential implications.
The risks of frozen pelvis surgery depend considerably on the severity of adhesions, the underlying disease and which organs are involved. Potential complications include:
Preparation for frozen pelvis surgery helps your surgical team assess the extent of pelvic disease, plan for possible organ involvement and ensure you are medically ready for the procedure. This may include:
After surgery, you will be monitored while recovering from general anaesthesia. Pelvic or abdominal discomfort is expected and can usually be managed with appropriate pain relief. You will be encouraged to begin moving when it is safe to do so and gradually resume eating and drinking. Instructions for incision care and activity will depend on the surgical approach and procedures performed.
Hospital discharge and subsequent recovery depend heavily on the extent of surgery. Recovery after minimally invasive adhesiolysis may be relatively straightforward, while extensive surgery involving endometriosis, the bowel, bladder or urinary tract may require a longer hospital stay and closer post-operative monitoring. Follow-up appointments allow your surgeon to assess healing and discuss further treatment where necessary.
There is no single recovery period for frozen pelvis surgery because the operation can range from minimally invasive adhesiolysis to complex surgery involving several pelvic organs. Patients undergoing limited minimally invasive surgery generally recover sooner than those requiring extensive dissection, organ-specific procedures or open surgery.
Recovery is influenced by the surgical approach, severity of adhesions, organs treated, any complications and your general health. The time required before returning to work also depends on the physical demands of your occupation, so activity should be increased gradually according to your surgeon's advice.
Yes. Adhesiolysis can divide existing adhesions and separate affected structures, but it cannot guarantee that adhesions will not develop again. Adhesions form as part of the body’s healing response, and pelvic or abdominal surgery itself can lead to new scar tissue formation.
The likelihood of further adhesions varies according to factors such as the underlying condition, extent of surgery and individual healing response. Recurrent adhesions do not necessarily cause symptoms or mean that another operation will be required.
Pregnancy may be possible after frozen pelvis surgery, but fertility depends on the underlying condition and the health of the uterus, ovaries and fallopian tubes. In selected women, releasing adhesions that distort reproductive anatomy may improve the possibility of natural conception.
However, surgery cannot guarantee pregnancy, particularly when severe endometriosis, tubal damage or other fertility factors are present. Some women may still require fertility treatment, including assisted reproductive techniques, following surgery.
A frozen pelvis occurs when extensive adhesions cause pelvic organs and tissues to become abnormally attached, often resulting in significant distortion of normal anatomy. Surgery may be considered when these adhesions cause persistent symptoms, affect surrounding organs or complicate conditions such as severe endometriosis.
Treatment typically involves adhesiolysis to carefully separate affected structures, together with treatment of the underlying disease where appropriate. Depending on the complexity of the condition, surgery may be performed laparoscopically, with robotic assistance or through open surgery.
Frozen pelvis surgery can relieve symptoms, restore pelvic anatomy where safely possible and address bowel, bladder, urinary or reproductive structures affected by severe adhesions. However, the complexity, benefits and risks vary considerably between patients, and adhesions can reform after surgery.
If you have been diagnosed with a frozen pelvis or severe pelvic adhesions, consider scheduling a consultation with Dr Ma Li to discuss your symptoms, treatment options and whether surgery may be appropriate for your individual condition.
No. A frozen pelvis describes extensive pelvic adhesions that cause organs to become fixed together. Severe endometriosis is an important cause, but frozen pelvis can also result from surgery, infection or other inflammatory processes.
It can be, particularly when dense adhesions involve multiple organs such as the bowel, bladder or ureters. The complexity varies substantially depending on the extent of pelvic disease.
There is no standard duration. Surgery involving limited adhesiolysis may take less time, while extensive adhesions or multi-organ involvement can make the operation considerably longer.
Not necessarily. However, if the bowel is extensively affected and bowel surgery may be required, another surgeon with appropriate expertise may be involved in the operation.
The hospital stay depends on the extent and type of surgery performed. Minimally invasive surgery may allow an earlier discharge, while complex or multi-organ surgery can require a longer stay.
This depends on the extent of surgery, your individual recovery and the physical demands of your job. Your surgeon can advise when it is appropriate to resume work and normal activities.
Treatment depends on the underlying condition and symptoms. Medications may help manage symptoms in some cases, particularly those related to endometriosis, but they do not physically divide established adhesions.
Repeat surgery may sometimes be necessary if significant symptoms or disease recur. Because further surgery can itself contribute to adhesion formation, the potential benefits and risks should be assessed carefully before another operation is considered.












