| Treatment | Excision of Endometriosis |
|---|---|
| Also known as | Endometriosis excision surgery, surgical excision of endometriosis |
| Used for | Endometriosis causing pelvic pain, painful periods, pain during intercourse, endometriomas or other significant symptoms where surgery is appropriate |
| How it works | Visible endometriosis lesions are surgically cut out from affected tissues and organs while preserving healthy tissue where possible |
| Anaesthesia | General anaesthesia |
| Surgical approach | Usually performed using minimally invasive laparoscopic or robotic-assisted surgery; open surgery may be required in selected complex cases |
| Hospital stay | Varies according to the extent and complexity of surgery and individual recovery |
| Downtime | Usually several weeks, depending on the extent of disease, surgery performed and individual recovery |
| Treatment course | Usually performed as a single surgical procedure followed by post-operative follow-up |
| Suitable for | Women with symptomatic or complex endometriosis for whom surgical removal of endometriosis lesions is considered appropriate after clinical assessment |
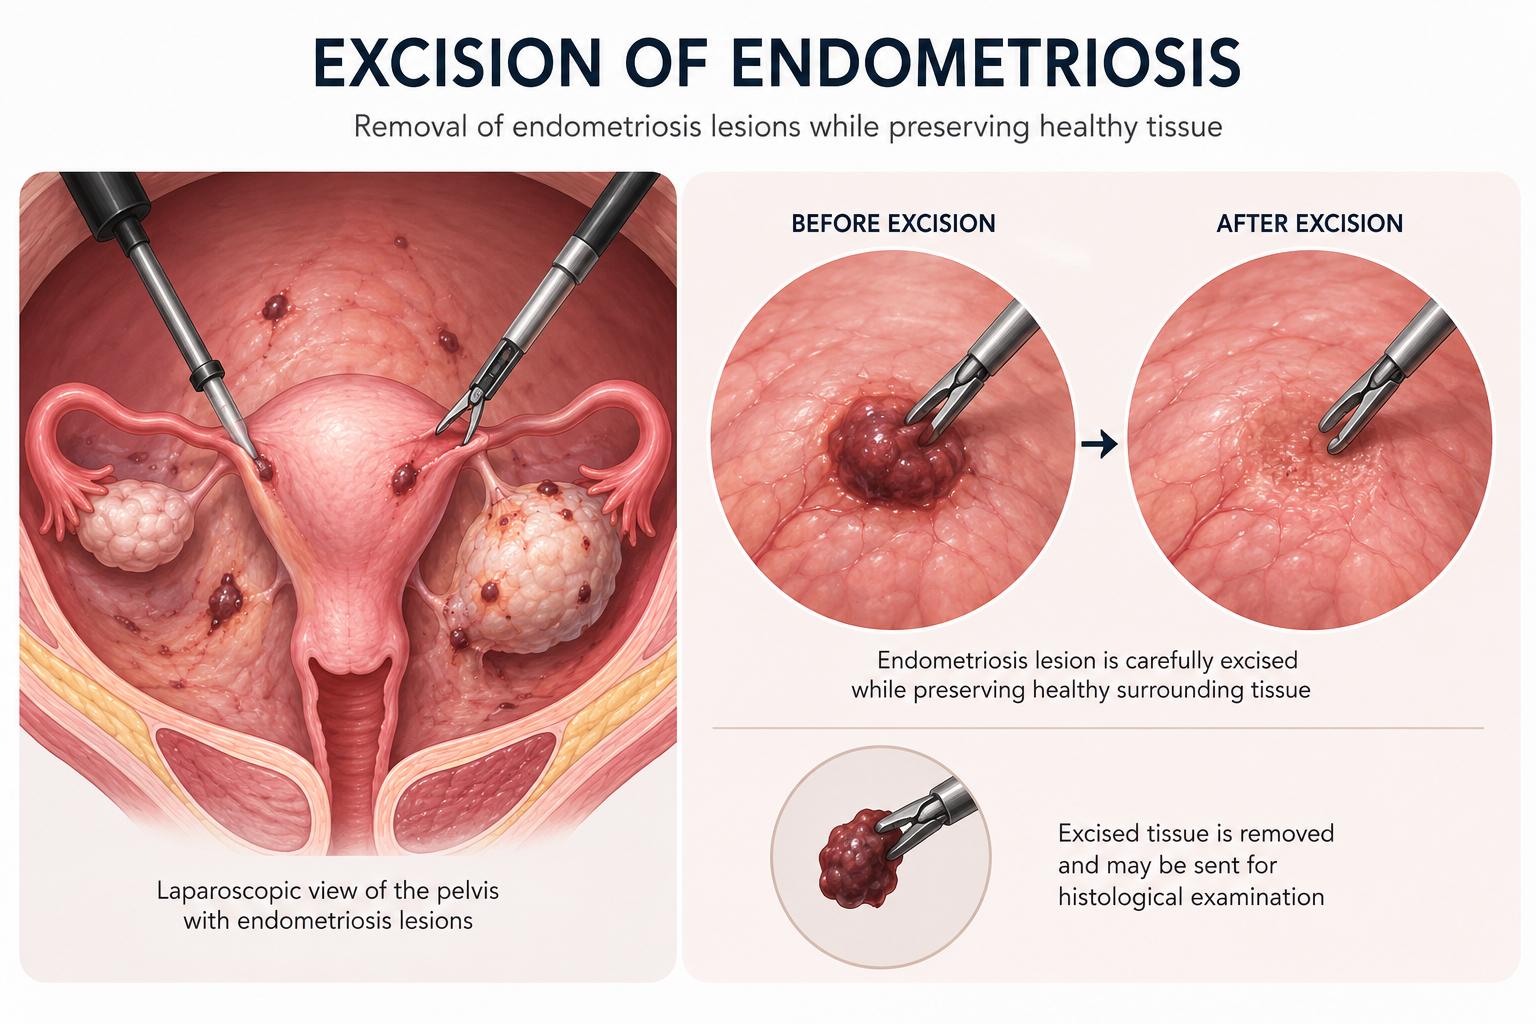
Endometriosis is a condition in which tissue similar to the lining of the uterus grows outside the uterus, commonly affecting structures within the pelvis. Excision of endometriosis is a surgical treatment in which visible endometriosis lesions are carefully cut out and removed from the affected tissues, while preserving healthy tissue and reproductive organs where possible.
Unlike ablation, which destroys endometriosis lesions using energy, excision physically removes the identified lesions and allows the removed tissue to be sent for histological examination when appropriate. Surgery can help manage endometriosis-related symptoms, but it does not guarantee that all symptoms will resolve permanently or that endometriosis will never recur.
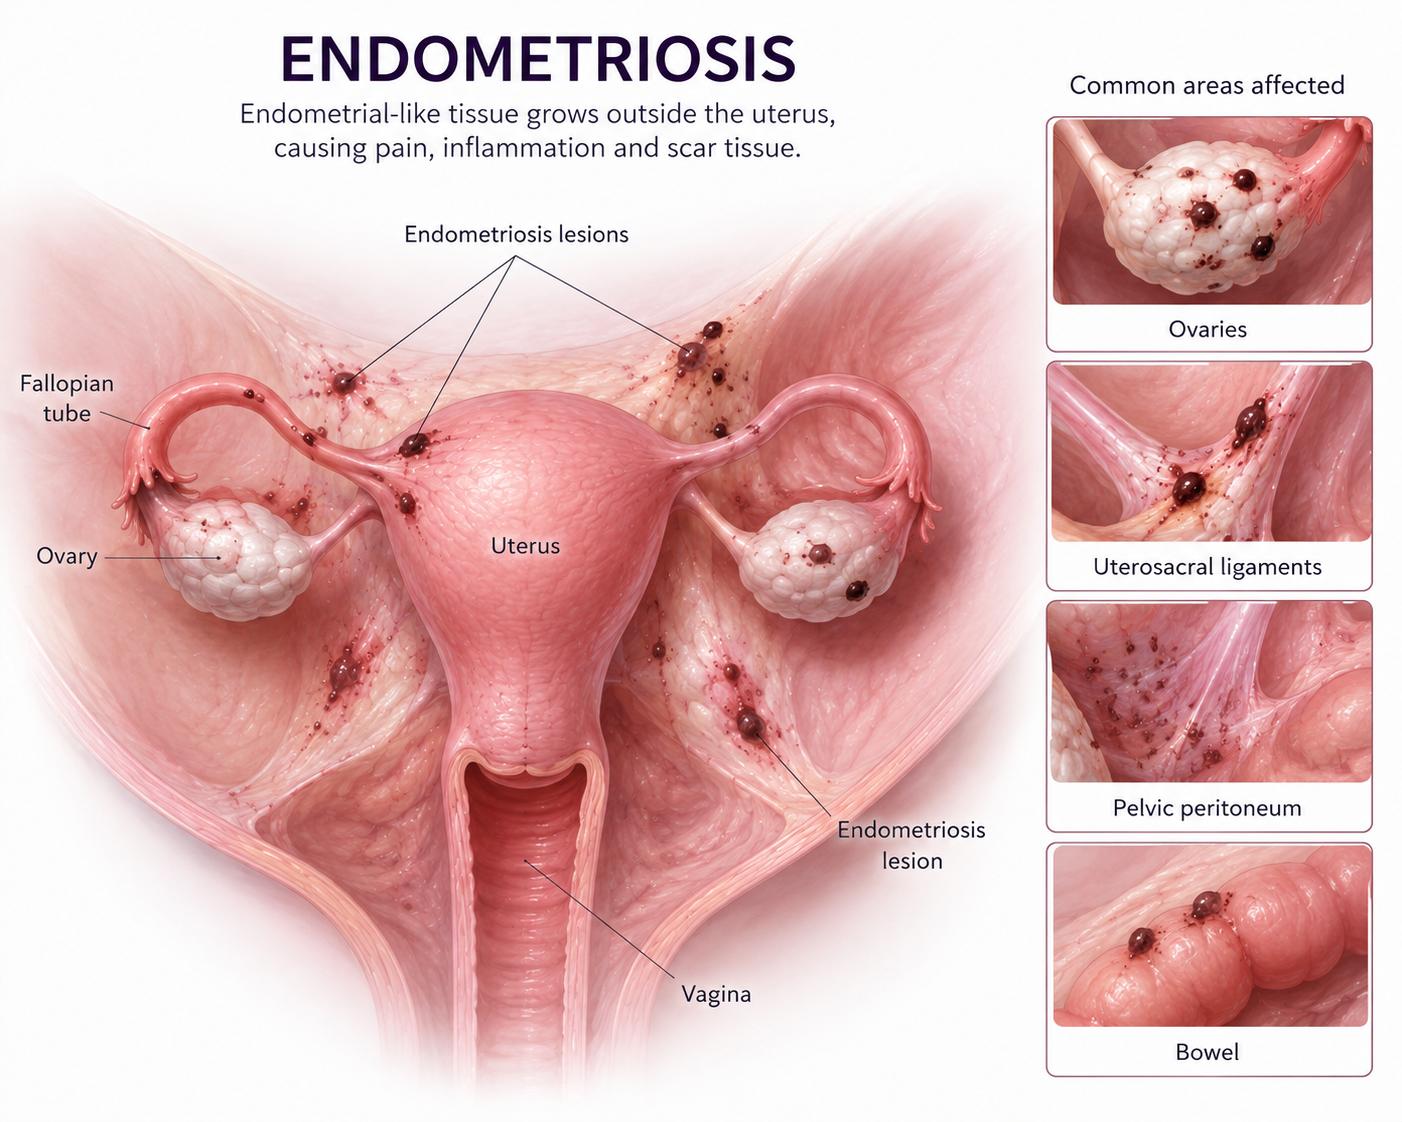
Not everyone with endometriosis requires surgery. Excision may be considered when symptoms are significant, medical treatment has not provided adequate relief, or the location and extent of the disease make surgical treatment appropriate.
Endometriosis excision surgery may be considered for women with:
The decision to proceed with surgery should take into account the severity of symptoms, location and extent of endometriosis, previous treatments, reproductive plans and individual preferences.
Both excision and ablation can be used to surgically treat endometriosis, but they manage the lesions differently. Excision removes affected tissue, while ablation uses energy to destroy endometriosis lesions.
| Excision | Ablation | |
|---|---|---|
| How Lesions Are Treated | Endometriosis lesions are surgically cut out | Energy is used to destroy the lesions |
| Treatment of Tissue | The affected tissue is physically removed | The lesion is destroyed without removing it in its entirety |
| Histological Examination | Removed tissue can be sent for laboratory examination | Tissue may not be available for histological examination after destruction |
| Suitability | May be used for superficial, ovarian or deep endometriosis depending on the individual case | May be considered for selected superficial lesions and, in some circumstances, ovarian endometriomas |
| Treatment Decision | Selected according to the type, depth and location of endometriosis and individual circumstances | Selected according to the type, depth and location of endometriosis and individual circumstances |
Excision is not automatically superior to ablation for every form of endometriosis. The appropriate technique depends on the type and location of the lesions, ovarian reserve and fertility considerations, the structures involved and the goals of treatment.
Endometriosis excision is usually performed using minimally invasive surgery. The surgical approach depends on the location and extent of the disease, previous surgery and whether other pelvic organs are involved.
Endometriosis excision is performed under general anaesthesia. The extent of the procedure varies according to where endometriosis is found and which tissues or organs are affected.
| Stage | What Happens |
|---|---|
| Pre-operative Preparation | Your medical history, investigations and medications are reviewed, and you receive instructions for preparing for surgery. |
| General Anaesthesia | Anaesthesia is administered so that you remain unconscious throughout the operation. |
| Surgical Access | Small abdominal incisions are usually made to introduce a camera and surgical instruments. |
| Pelvic Examination | The surgeon systematically examines the pelvis and relevant organs to identify areas affected by endometriosis. |
| Identifying Endometriosis | Visible endometriosis lesions and affected tissues are identified before treatment. |
| Excising the Lesions | Identified lesions are carefully cut out while preserving surrounding healthy structures where possible. |
| Treating Affected Structures | Additional surgical treatment may be required if endometriosis involves the ovaries or other pelvic structures. |
| Recovery and Monitoring | The instruments are removed, incisions are closed and you are monitored as you recover from anaesthesia. |
Endometriosis can affect different structures within the pelvis, so the extent of excision varies considerably between patients. Depending on where the disease is located, surgery may involve:
Deep endometriosis involving the bowel, bladder, ureters or other organs requires careful surgical planning. Depending on the location and extent of disease, treatment may involve a multidisciplinary team with expertise in the affected organs.
Endometriosis excision aims to remove visible areas of endometriosis while preserving healthy surrounding tissues where possible. For appropriately selected patients, potential benefits include:
The benefits vary according to the location and extent of endometriosis and individual patient factors. Excision does not guarantee complete or permanent symptom relief, and endometriosis or associated symptoms may persist or recur after surgery.
Endometriosis excision surgery may be considered when symptoms are persistent or significantly affect daily life, particularly when medical treatment has not provided adequate relief. It may be appropriate for women with:
The decision to undergo endometriosis excision should take into account the extent of the disease, symptoms, reproductive plans and available alternatives. Important considerations include:
As with any surgical procedure, endometriosis excision carries potential risks. These vary according to the location and extent of endometriosis, the organs involved and the complexity of the surgery.
Preparation for endometriosis excision surgery helps your surgical team assess the extent of the disease, plan the procedure and ensure you are medically ready for surgery. Depending on your individual circumstances, this may include:
After surgery, you will be monitored as you recover from general anaesthesia. Some abdominal or pelvic discomfort is expected and can usually be managed with pain relief. You will generally be encouraged to start moving when it is safe to do so and gradually resume eating and drinking. If laparoscopic or robotic surgery was performed, you will also receive instructions on caring for the small abdominal incisions.
Discharge from hospital depends on the extent of surgery and how well you recover. Recovery following limited excision may be relatively straightforward, while extensive endometriosis involving the bowel, bladder, ureters or multiple pelvic structures can require a longer hospital stay and recovery period. Follow-up appointments are arranged to assess healing, review any histology results and discuss further management where required.
There is no single recovery period for endometriosis excision because the extent of surgery can vary considerably. Recovery after uncomplicated minimally invasive surgery may take around 2 to 4 weeks, while more extensive surgery involving deep endometriosis or multiple pelvic organs may require a longer recovery.
Your general health, the amount of tissue removed, organs involved, surgical approach and any complications can all influence recovery. Returning to work also depends on the physical demands of your occupation, so activity should be increased gradually according to your surgeon's advice.
Yes. Excision removes endometriosis lesions identified during surgery, but it does not guarantee that endometriosis will never return. Some lesions may be difficult to identify or safely remove, and new or recurrent disease can occur over time.
Symptoms may also persist or recur after surgery, particularly because pelvic pain can have multiple causes. Depending on your symptoms, reproductive plans and individual risk of recurrence, ongoing medical treatment or further surgery may sometimes be required.
Yes, pregnancy may be possible after endometriosis excision because the uterus and reproductive organs are preserved where clinically possible. In selected women with endometriosis-associated infertility, surgery may improve the chance of spontaneous pregnancy, although the effect depends on factors such as age, extent of disease and other causes of infertility.
Pregnancy cannot be guaranteed after surgery. When endometriosis involves the ovaries, particularly ovarian endometriomas, surgery can also affect ovarian reserve. Fertility goals should therefore be discussed before surgery so that treatment can be planned with future pregnancy in mind.
Endometriosis excision surgery removes visible endometriosis lesions from affected tissues while preserving healthy tissue and reproductive organs where possible. Usually performed through minimally invasive laparoscopic or robotic-assisted surgery, excision may be considered for persistent pain, ovarian endometriomas, deep endometriosis or disease affecting surrounding pelvic structures when surgery is clinically appropriate.
For selected patients, it can reduce endometriosis-related symptoms and improve quality of life.
However, the outcome depends on the location and extent of disease, organs involved and individual circumstances, and surgery cannot guarantee permanent relief or prevent endometriosis from recurring.
Fertility goals, alternative treatments and the potential risks of surgery should therefore form part of treatment planning. If you are considering endometriosis excision surgery in Singapore, schedule a consultation with Dr Ma Li to discuss your symptoms, treatment options and whether surgical excision may be appropriate for you.
It can be, depending on the extent and location of endometriosis. Limited laparoscopic excision may be relatively straightforward, while deep endometriosis involving multiple organs can require complex surgery.
The duration varies considerably according to the amount and location of endometriosis and whether other pelvic organs require treatment. More extensive or complex disease generally requires a longer operation.
Some patients undergoing uncomplicated minimally invasive surgery may be discharged the same day or after an overnight stay. More extensive surgery may require several days in hospital.
This depends on the extent of surgery, your recovery and the nature of your work. Patients with physically demanding jobs may require more time away from work than those returning to less strenuous activities.
Gentle walking is generally encouraged during early recovery, while strenuous exercise and heavy lifting should be avoided initially. Your surgeon will advise when you can safely increase your activity.
The appropriate timing depends on the extent and location of surgery and how well you are healing. Your surgeon can advise when vaginal intercourse can be safely resumed during follow-up.
Possibly. Hormonal treatment may be recommended after surgery for some women to manage symptoms or reduce the risk of recurrence, particularly when pregnancy is not being attempted immediately.
Yes, repeat surgery may sometimes be considered if endometriosis or significant symptoms recur. However, the benefits and risks of further surgery, including possible effects on fertility and ovarian reserve, should be assessed carefully.












