

| Definition | Endometriosis that extends into deeper tissues and may involve nearby pelvic organs. |
|---|---|
| Common locations | Uterosacral ligaments, rectovaginal region, bowel, bladder, ureters and pelvic sidewall. |
| Symptoms | Severe period pain, pelvic pain, painful intercourse, bowel or urinary symptoms and fertility difficulties. |
| Diagnosis | Clinical assessment with specialist ultrasound and/or MRI where appropriate. |
| Treatment | Medication, fertility-directed management or surgery depending on symptoms, disease location and individual goals. |
The condition occurs when tissue similar to the lining of the uterus grows outside the uterus. It most commonly develops within the pelvis, where it can affect the ovaries, pelvic lining and tissues around the reproductive organs.
In deep infiltrating endometriosis, the disease grows more deeply into the tissues rather than remaining on the surface. It may cause inflammation, scarring and adhesions, and can sometimes involve nearby organs.
Deep endometriosis is not defined simply by how painful the symptoms are. Some women with extensive disease may have relatively few symptoms, while others may experience significant pain despite less extensive disease. The location of the lesions and the structures involved are therefore important when assessing the condition.
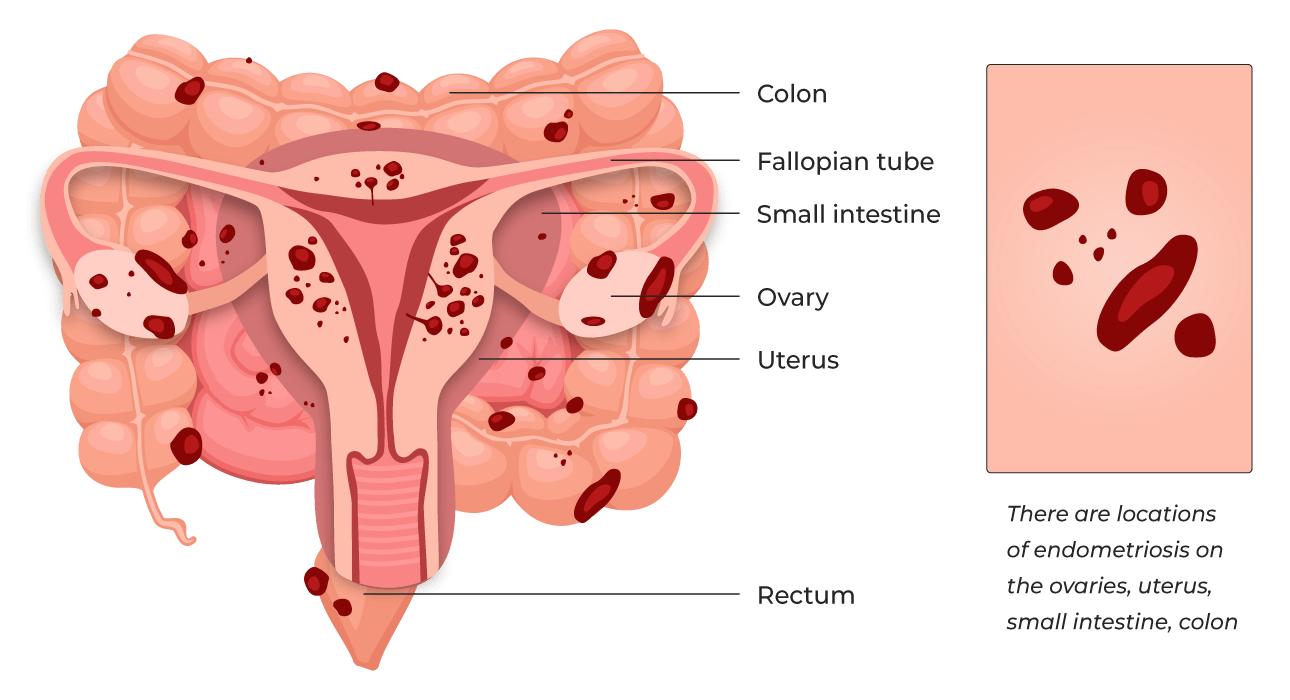
Deep infiltrating endometriosis can develop in different parts of the pelvis and, less commonly, outside the pelvic cavity. The location of the disease can influence the type of symptoms a woman experiences, particularly when nearby organs or nerves are affected.
Some of the areas that may be involved include:
The symptoms of deep infiltrating endometriosis can vary depending on where the disease is located and which structures are affected. Common symptoms include:
Some women may have extensive deep endometriosis with relatively few symptoms, while others may experience significant pain despite having less extensive disease. Symptoms can also overlap with conditions affecting the bowel, bladder or reproductive organs, which can make diagnosis more challenging.
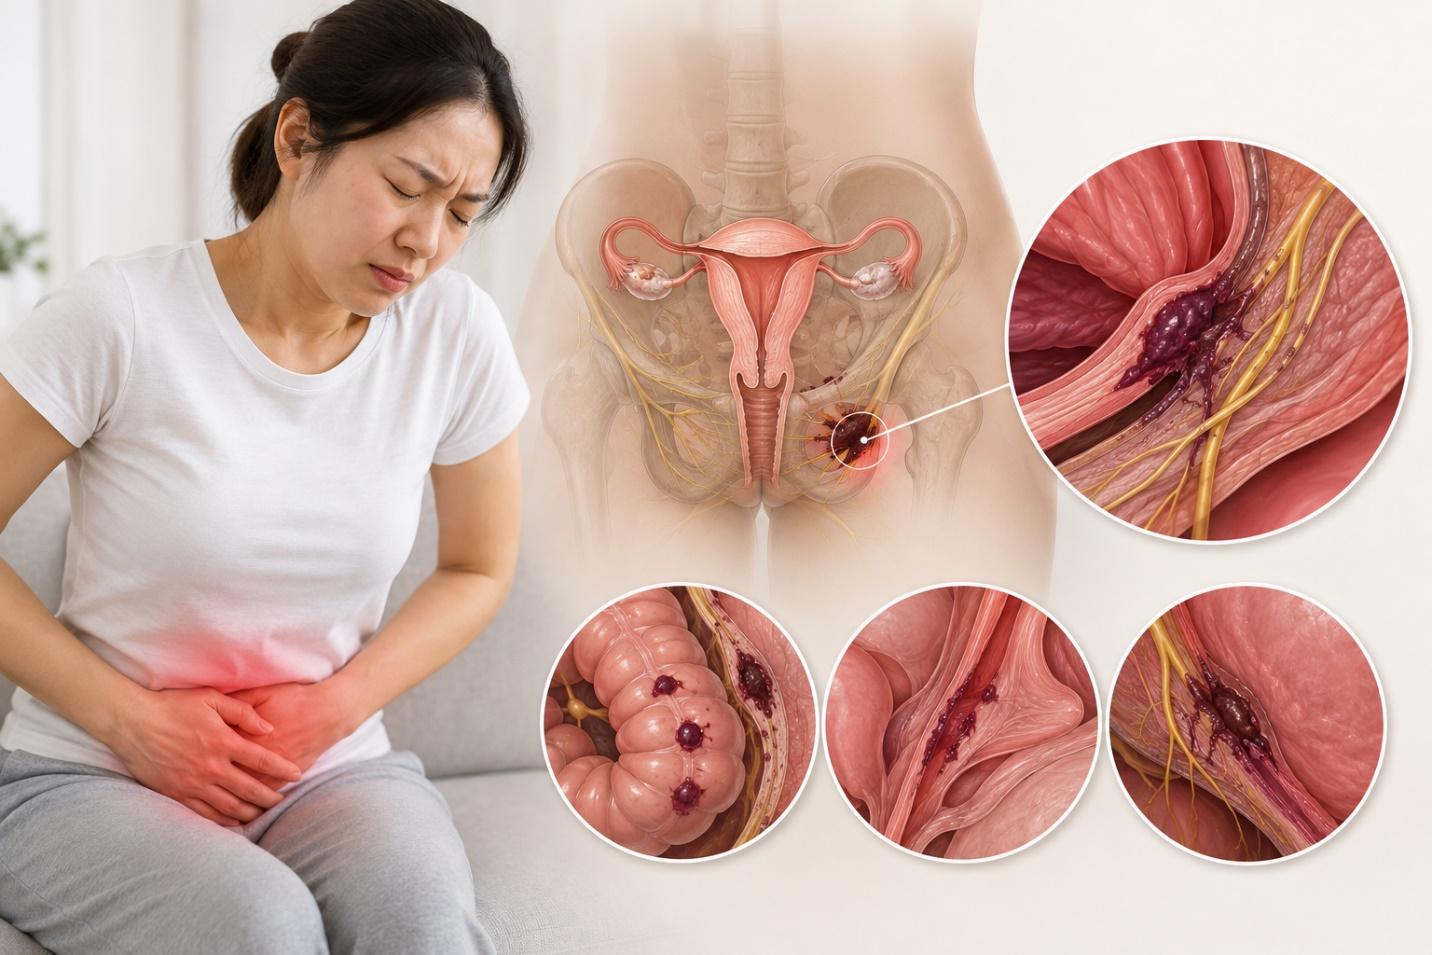
Pelvic pain is one of the most recognised symptoms of deep infiltrating endometriosis. However, the nature and severity of the pain can differ depending on where the disease is located.
Some women describe the pain as sharp, stabbing or deeply aching, while others experience a persistent sensation of pressure, heaviness or discomfort within the pelvis. Pain may become particularly pronounced during menstruation, but deep endometriosis can also cause chronic pelvic pain outside of the menstrual period.
When endometriosis affects the tissues between or around the vagina and rectum, women may experience pain during sexual intercourse or bowel movements. Bowel or bladder involvement can also produce symptoms that become more noticeable during menstruation.
Persistent pelvic pain can affect far more than physical comfort. It may interfere with work, relationships, sleep, exercise and everyday activities, significantly affecting a woman's overall quality of life.
Endometriosis is associated with reduced fertility in some women, although having deep infiltrating endometriosis does not mean that natural conception is impossible.
Several factors may contribute to difficulties becoming pregnant. These can include:
The impact on fertility can vary significantly between individuals. The location and extent of endometriosis, ovarian reserve, age and other reproductive factors all need to be considered when assessing fertility.
For women who are hoping to become pregnant, understanding the extent and location of endometriosis can therefore be an important part of treatment planning. Depending on the individual circumstances, management may involve medical treatment, fertility treatment, surgery or a combination of approaches.
For women hoping to conceive, treatment planning should consider age, ovarian reserve, symptoms, disease location, previous surgery and other fertility factors. Surgery is not automatically required to improve fertility in women with deep endometriosis; depending on the circumstances, fertility treatment, surgery or a combination of approaches may be considered.

A thorough assessment may include:
Ultrasound and MRI can identify many cases of deep endometriosis, but a normal scan does not exclude every form of endometriosis, particularly superficial disease.

Treatment for deep infiltrating endometriosis depends on the location and extent of disease, the severity of symptoms, previous treatments, fertility plans and the woman's individual goals. Treatment may include medication to manage symptoms and suppress disease activity, as well as surgery for selected patients.
Surgery may be considered when symptoms remain significant despite medical treatment, when deep endometriosis affects important pelvic structures, or when the extent and location of disease make surgical treatment appropriate.
For complex cases, careful assessment and planning are important, particularly when the bowel, bladder, ureters or other pelvic structures are involved.
For complex endometriosis, the goal is not simply to remove visible disease, but to plan surgery carefully while taking into consideration the surrounding organs and preservation of healthy tissue where appropriate.

Deep infiltrating endometriosis can involve multiple pelvic structures and may require careful assessment and surgical planning. Dr Ma Li has a particular interest in complex gynaecological surgery, including minimally invasive and robotic-assisted approaches for appropriately selected patients.
Where surgery is recommended, the surgical approach is considered based on the location and extent of endometriosis, the organs involved, previous procedures, fertility considerations and the individual's treatment goals.
If you have symptoms suggestive of deep infiltrating endometriosis or have already been diagnosed with extensive disease, a specialist assessment can help you understand your condition and the treatment options available to you.
Book a consultation with Dr Ma Li to discuss your symptoms, diagnosis and treatment options.

It can be more complex because disease may involve or grow close to important pelvic structures. “Deep” describes location and depth rather than automatically indicating symptom severity.
Endometriosis can recur after treatment. The likelihood varies with disease extent, treatment and hormonal environment, so long-term follow-up may be appropriate.
Symptoms may improve as hormone levels decline, but existing disease does not necessarily disappear immediately. Symptoms after menopause should be assessed.
Endometriosis is benign and the vast majority of women do not develop cancer. Some rare ovarian cancers are associated with endometriosis, but the overall risk remains low.
No. Management depends on symptoms, disease location, previous treatment, fertility plans and the effect on quality of life.
Yes. Symptoms may overlap with bowel, bladder, reproductive and other pelvic conditions, which can delay diagnosis.
No. It is one approach for selected complex cases. Suitability depends on disease location and extent, previous surgery, involved structures and the overall treatment plan.
It can affect the ureters. If a ureter becomes narrowed or obstructed, kidney function may be affected, so suspected ureteric disease requires careful assessment.
Yes. Pain severity does not always correspond to disease extent. Extensive disease may cause mild symptoms, while less extensive disease can cause significant pain.
No. Deep endometriosis describes disease type and location; Stage 4 describes overall extent under a staging system. Either may occur without the other.
| Element | Deep endometriosis | Stage 4 endometriosis |
|---|---|---|
| Describes | Depth / location | Overall extent |
| May involve organs? | Yes | Yes, but not necessarily |
| Automatically the same? | No | No |
| Predicts pain severity? | No | No |
















