| Treatment | Surgery for Bowel Endometriosis |
|---|---|
| Used for | Bowel endometriosis causing significant pain, bowel symptoms or other complications where surgical treatment is appropriate |
| How it works | Endometriosis affecting the bowel is surgically removed using a technique selected according to the location, depth and extent of disease |
| Anaesthesia | General anaesthesia |
| Surgical approach | Usually laparoscopic or robotic-assisted surgery; open surgery may be required in selected complex cases |
| Surgical techniques | Superficial shaving, disc excision or segmental bowel resection, depending on the extent and depth of bowel involvement |
| Hospital stay | Varies according to the type and extent of bowel surgery and individual recovery |
| Downtime | Usually several weeks, depending on the procedure performed, complexity of surgery and individual recovery |
| Treatment course | Usually performed as a single surgical procedure with post-operative follow-up |
| Suitable for | Women with symptomatic bowel endometriosis for whom surgery is considered appropriate after specialist assessment |
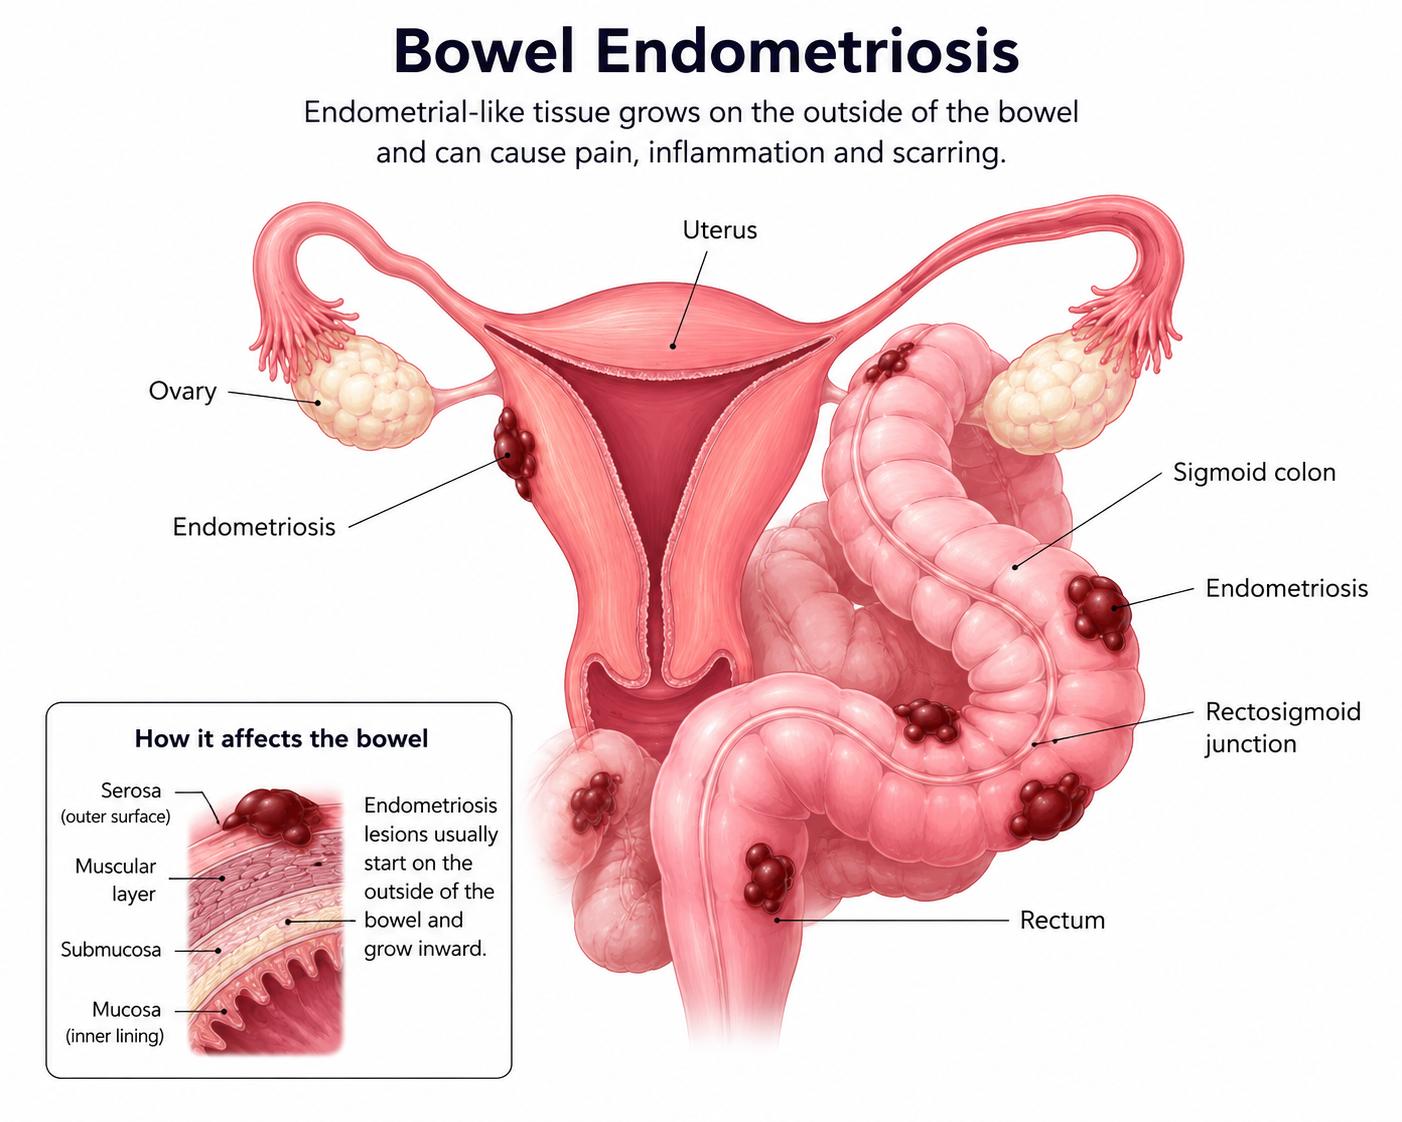
Bowel endometriosis occurs when endometriosis affects the bowel, most commonly the rectum and sigmoid colon. It is a form of deep endometriosis in which lesions typically develop on the outer surface of the bowel and may extend into the deeper muscular layers of the bowel wall, instead of originating from its inner lining.
As the disease progresses, inflammation and fibrosis can cause the bowel to become attached to surrounding pelvic structures through adhesions. In more extensive cases, endometriosis can thicken or distort the bowel wall and narrow the passage through which bowel contents move.
Symptoms vary according to the location and extent of bowel involvement and may become more noticeable around menstruation. Women with bowel endometriosis may experience:

Diagnosis begins with a detailed medical and gynaecological history, including the type of bowel symptoms experienced and whether they change during the menstrual cycle. A pelvic examination may also be performed where appropriate to identify tenderness, reduced organ mobility or findings suggestive of deep endometriosis.
Specialist transvaginal ultrasound can help identify and assess deep endometriosis involving the bowel, while MRI may be used to map the location and extent of disease and its relationship with surrounding pelvic structures. When surgery is performed, the affected areas can be directly assessed and removed tissue may be sent for histological examination.
Colonoscopy is not routinely used to diagnose bowel endometriosis because the disease generally develops on the outside of the bowel and grows inward, while colonoscopy primarily examines the inner bowel lining. It may, however, be used when clinically indicated to investigate other possible causes of bowel symptoms.
Not everyone diagnosed with bowel endometriosis requires an operation. Surgery may be considered when symptoms are significant, medical treatment has not provided adequate control or the disease is causing substantial bowel involvement. It may be appropriate for women with:
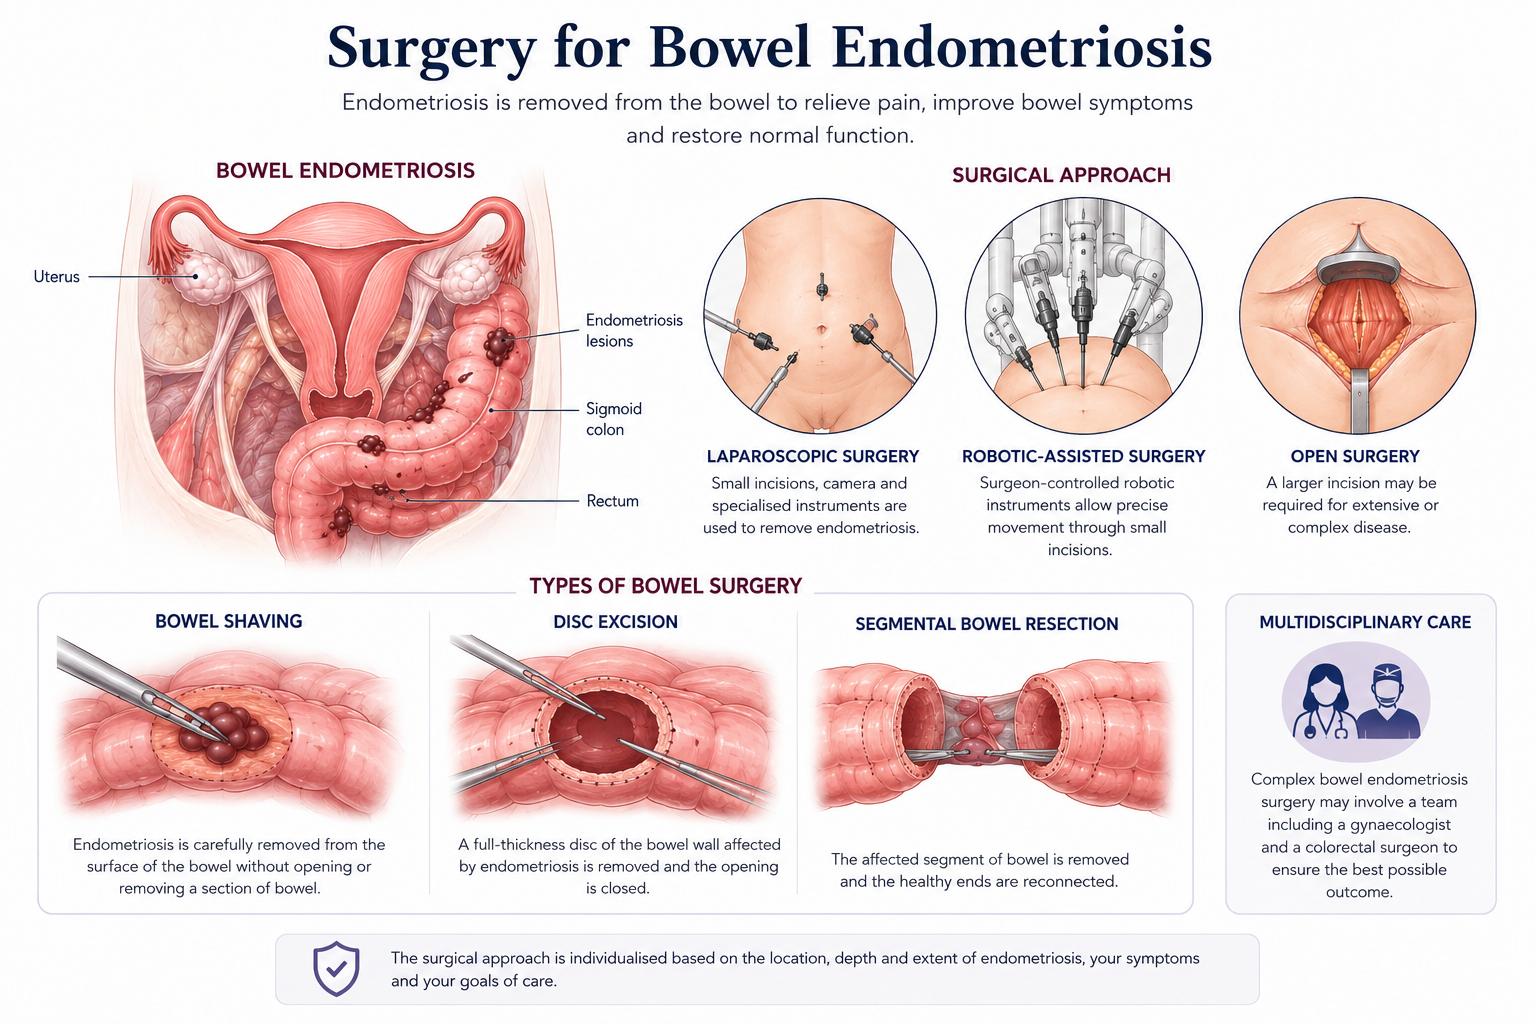
The surgical technique is selected according to factors such as the size, depth, number and location of bowel lesions and the degree to which the bowel wall is affected. The main surgical techniques include:
Bowel endometriosis surgery is commonly performed using a minimally invasive approach, although the technique depends on the extent and complexity of the disease and the bowel procedure required.
Because bowel endometriosis may involve both gynaecological and colorectal structures, surgical planning may involve a multidisciplinary team. A colorectal surgeon may participate when more extensive bowel surgery, such as disc excision or segmental resection, is anticipated.
The exact procedure depends on the location, depth and extent of bowel endometriosis. Surgery is performed under general anaesthesia and may also involve treatment of endometriosis elsewhere in the pelvis.
| Stage | What Happens |
|---|---|
| Pre-operative Preparation | Your medical history, imaging results and planned procedure are reviewed before surgery. |
| General Anaesthesia | Anaesthesia is administered so that you remain unconscious throughout the operation. |
| Surgical Access | The abdomen and pelvis are accessed using the planned laparoscopic, robotic-assisted or open approach. |
| Assessment of Disease | The bowel and surrounding pelvic structures are examined to determine the extent of endometriosis. |
| Assessment of Bowel Lesions | The location, depth and extent of bowel wall involvement are evaluated. |
| Removal of Endometriosis | Bowel shaving, disc excision or segmental resection is performed according to the extent of disease. |
| Treatment of Other Endometriosis | Endometriosis affecting other pelvic structures may also be removed where appropriate. |
| Completion and Recovery | The operation is completed, surgical sites are closed and post-operative monitoring begins. |
Bowel endometriosis most frequently affects the lower part of the large bowel, particularly the rectum and rectosigmoid region. Areas that may be involved include:
The location of disease is important because it can influence symptoms, surgical planning and the type of procedure required.
Surgery aims to remove bowel endometriosis and address symptoms or complications associated with the disease. Potential benefits for appropriately selected patients include:
Outcomes vary according to the extent of disease, procedure performed and individual circumstances. Surgery cannot guarantee complete or permanent relief, and symptoms or endometriosis may persist or recur.
Surgery may be considered when bowel endometriosis causes significant symptoms or complications and the expected benefits of treatment justify the risks of surgery. It may be appropriate for women with:
The extent of bowel surgery can vary considerably between patients, making careful pre-operative planning particularly important. Factors to consider include:
Risks vary substantially according to the extent of disease and the procedure performed. Superficial bowel shaving generally involves different risks from full-thickness disc excision or segmental bowel resection.
Preparation helps establish the extent of bowel and pelvic disease, determine the planned procedure and ensure you are medically ready for surgery. Depending on your individual circumstances, this may include:
After surgery, you will be monitored as you recover from general anaesthesia and given appropriate pain relief. You will usually be encouraged to start moving when safe, while eating and drinking are gradually resumed according to your recovery and the bowel procedure performed. Your surgical team will also monitor bowel and urinary function and provide instructions for caring for your incisions.
The hospital stay and early recovery depend considerably on the extent of surgery. Recovery after bowel shaving may differ from recovery after full-thickness disc excision or segmental bowel resection. Before discharge, you will receive guidance on diet, physical activity, wound care and symptoms that require medical attention, with follow-up arranged to assess your recovery.
There is no single recovery period because bowel endometriosis surgery ranges from relatively limited excision to segmental bowel resection combined with treatment of extensive pelvic endometriosis. The type of bowel procedure, amount of disease removed and any additional pelvic surgery all influence how quickly you recover.
Your surgical approach, general health and whether complications occur also affect recovery. Returning to work depends on both the extent of surgery and the physical demands of your occupation, so activities should be resumed gradually according to your surgeon's advice.
Most patients undergoing surgery for bowel endometriosis do not require a stoma. Bowel shaving does not involve removal of a bowel segment, while many patients undergoing disc excision or segmental resection can also have the bowel repaired or reconnected without a stoma.
However, a temporary stoma may occasionally be considered in selected complex cases, particularly when it is needed to protect a bowel connection or reduce the consequences of a potential leak. If there is a meaningful possibility that a stoma may be required, this should be discussed with you before surgery.
Surgery removes the bowel endometriosis identified and treated during the operation, but it does not guarantee a permanent cure. Endometriosis can persist or recur, and symptoms may also return over time.
Further management depends on your symptoms, reproductive plans and individual circumstances. Some patients may benefit from ongoing medical treatment after surgery, while further surgical treatment may occasionally be considered if significant disease or symptoms recur.
Bowel endometriosis occurs when endometriosis affects the bowel, most commonly the rectum and rectosigmoid region. Surgery may be considered when the condition causes significant pain or bowel symptoms, results in substantial bowel narrowing or does not respond adequately to conservative treatment.
Depending on the depth and extent of disease, treatment may involve bowel shaving, disc excision or segmental bowel resection, usually through a minimally invasive laparoscopic or robotic-assisted approach where appropriate. The aim of surgery is to remove endometriosis, relieve symptoms and address bowel involvement while avoiding unnecessary bowel resection where possible.
However, bowel endometriosis surgery can be complex, particularly when deep disease affects several pelvic structures, and treatment must balance potential benefits against bowel-specific surgical risks and the possibility of recurrence.
If you are considering surgery for bowel endometriosis in Singapore, schedule a consultation with Dr Ma Li to discuss your symptoms, the extent of your condition and the surgical approach most appropriate for your needs.
No. Endometriosis is a condition involving endometriosis-like tissue outside the uterus, whereas IBS is a disorder of gut-brain interaction. However, some symptoms can overlap and both conditions can occur together.
Often, no. Bowel endometriosis usually affects the bowel from the outside inward and may not reach the inner lining examined during colonoscopy.
No. Depending on the depth and extent of disease, endometriosis may be treated with bowel shaving or disc excision without removing an entire segment of bowel.
The duration varies according to the extent of disease and the procedure required. Surgery involving multiple pelvic structures or bowel resection generally takes longer than limited excision.
A colorectal surgeon may be involved when significant bowel surgery is anticipated. This depends on the location and extent of bowel involvement and the planned procedure.
Eating and drinking are usually resumed progressively after surgery according to your recovery and the bowel procedure performed. Your surgical team will provide specific dietary guidance.
This depends on the type and extent of surgery, your recovery and the physical demands of your job. More extensive bowel surgery generally requires a longer period away from work.
Yes, although complete obstruction is uncommon. Deep endometriosis can cause fibrosis and narrowing of the bowel, which may occasionally become severe enough to obstruct the passage of bowel contents.










