| Treatment | Surgery for Ureter & Bladder Endometriosis |
|---|---|
| Used for | Endometriosis affecting the bladder or ureters, particularly when it causes significant symptoms, urinary obstruction or risks affecting kidney function |
| How it works | Removes endometriosis affecting the urinary tract and, where necessary, repairs or reconstructs the bladder or ureter to maintain urinary function |
| Anaesthesia | General anaesthesia |
| Surgical approach | Laparoscopic, robotic-assisted or open surgery, depending on the location and complexity of the disease |
| Procedures | Bladder excision, partial cystectomy, ureterolysis, ureteric resection and reconnection, or ureteric reimplantation, as clinically appropriate |
| Hospital stay | Varies according to the extent of surgery, urinary tract involvement and individual recovery |
| Recovery | Depends on the procedure performed, extent of endometriosis and whether bladder or ureteric reconstruction is required |
| Treatment course | Usually performed as a single surgical procedure, followed by post-operative monitoring and follow-up |
| Suitable for | Patients with bladder or ureteric endometriosis for whom surgical treatment is considered appropriate after specialist assessment |
Ureter and bladder endometriosis are forms of urinary tract endometriosis, where endometriosis affects structures involved in storing or transporting urine. Bladder endometriosis typically involves the bladder wall, while ureteric endometriosis affects one or both ureters, the tubes that carry urine from the kidneys to the bladder.
Ureteric endometriosis may develop around the outside of the ureter, where fibrosis and scarring can compress it or infiltrate the ureteric wall itself. This can cause narrowing or obstruction and interfere with the flow of urine from the kidney to the bladder, potentially affecting kidney function if left untreated. Importantly, ureteric obstruction can sometimes develop with few or no noticeable urinary symptoms.
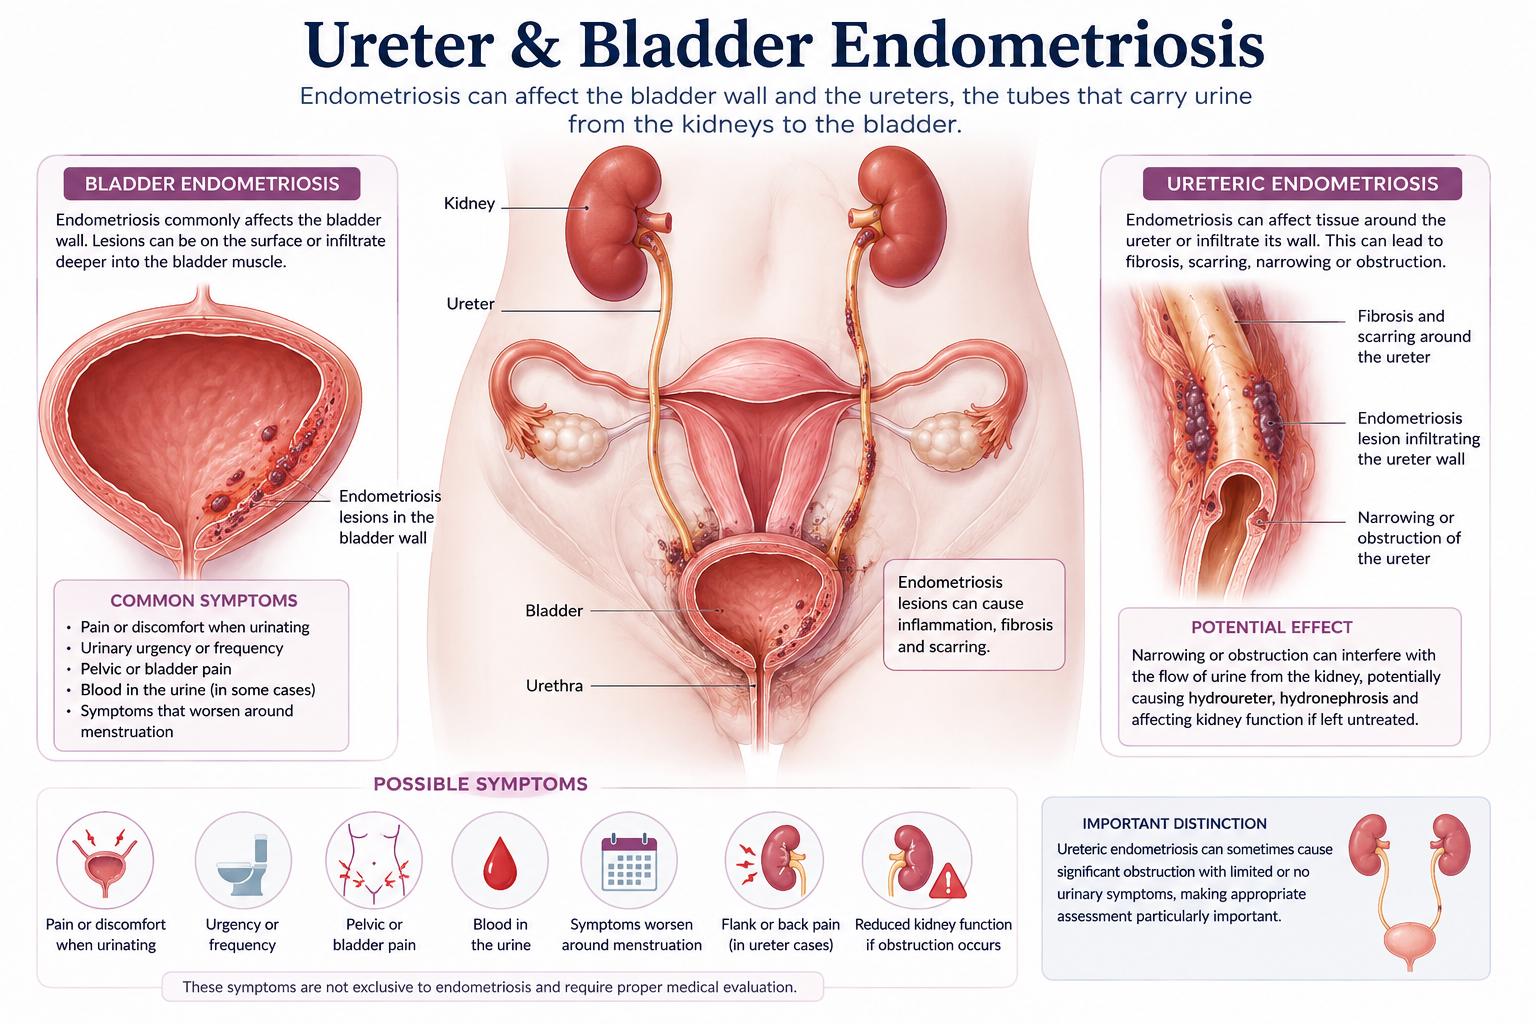

Symptoms depend on whether endometriosis affects the bladder, ureters or other pelvic structures at the same time. Some symptoms may become more noticeable around menstruation.
Bladder-related symptoms may include:
Ureter-related symptoms may include:
These symptoms are not specific to endometriosis and can occur with other urinary or gynaecological conditions. Proper assessment is therefore important to identify their underlying cause.
Diagnosis begins with a detailed medical and gynaecological history, including urinary symptoms, pelvic pain and whether symptoms change during the menstrual cycle. A pelvic examination may also be performed where clinically appropriate.
Specialist ultrasound can help identify deep endometriosis and assess possible involvement of the bladder or ureters. When ureteric disease is suspected, the kidneys and urinary tract may also be evaluated for impaired urine drainage, including hydroureter or hydronephrosis. MRI may be used to map deep endometriosis and determine its relationship with the bladder, ureters and surrounding pelvic structures. Kidney function may also be assessed when ureteric obstruction is suspected.
Cystoscopy, which uses a small camera to examine the inside of the bladder, may be performed in selected cases but is not required for every patient. Investigations are used not only to establish the location and extent of endometriosis, but also to determine whether urinary drainage or kidney function has been affected.
Not everyone with urinary tract endometriosis requires surgery. Treatment is individualised according to symptoms, the extent of disease and whether the urinary tract or kidney function is at risk. Surgery may be considered for women who:
Ureteric endometriosis requires particular attention because obstruction can sometimes progress without prominent symptoms. In these cases, preserving urinary drainage and protecting kidney function may become an important reason for surgical intervention.
The type of surgery depends on the size, depth and location of the bladder lesion and its relationship with nearby structures, particularly where the ureters enter the bladder.
The appropriate technique is selected according to the depth and extent of bladder involvement, the location and size of the lesion, and its proximity to the ureteric openings.
Surgery for ureteric endometriosis aims to remove or release disease affecting the ureter, relieve obstruction and preserve urine drainage from the kidney where possible. The procedure required depends on whether endometriosis surrounds or infiltrates the ureter and the location and extent of the affected segment.
There is no single surgical technique that is suitable for every patient with ureteric endometriosis. The procedure is selected according to the location and extent of disease, severity and length of ureteric narrowing, degree of obstruction, and the condition of the affected ureter and kidney.
Surgery is usually performed using a minimally invasive approach, although the method depends on the location and extent of endometriosis, the urinary structures affected and whether repair or reconstruction is required.
When endometriosis significantly affects the ureters or bladder, multidisciplinary surgical planning with a urologist may be required.
The exact procedure varies according to the structures affected and the extent of disease. Surgery is performed under general anaesthesia and may include treatment of endometriosis elsewhere in the pelvis.
| Stage | What Happens |
|---|---|
| Pre-operative Preparation | Your medical history, imaging, urinary tract assessment and planned surgical procedure are reviewed. |
| General Anaesthesia | Anaesthesia is administered so that you remain unconscious throughout the operation. |
| Surgical Access | The abdomen and pelvis are accessed using the planned surgical approach. |
| Assessment of Disease | The bladder, ureters and surrounding pelvic structures are carefully examined. |
| Identification of Endometriosis | The location, depth and extent of urinary tract involvement are assessed. |
| Removal of Endometriosis | Endometriosis affecting the bladder or ureters is carefully excised where appropriate. |
| Repair or Reconstruction | Bladder repair, ureteric reconstruction or ureteric reimplantation may be performed when required. |
| Completion and Recovery | The operation is completed, surgical sites are closed and post-operative monitoring begins. |
Surgery aims to remove urinary tract endometriosis, relieve associated symptoms and, where ureteric obstruction is present, restore urinary drainage and protect kidney function. Potential benefits include:
Outcomes depend on the severity and location of disease and the procedure required. Surgery cannot guarantee complete or permanent symptom relief, and endometriosis may persist or recur.
The extent of urinary tract involvement can vary considerably, so careful assessment is needed before deciding on surgery. Important considerations include:
The risks of surgery depend considerably on the extent of endometriosis and whether the procedure involves limited excision, partial cystectomy or ureteric reconstruction. Potential complications include:
Preparation helps determine the extent of urinary tract involvement, plan the appropriate procedure and ensure you are medically ready for surgery. Depending on your individual circumstances, this may include:
After surgery, you will be monitored as you recover from general anaesthesia and provided with appropriate pain relief. You will usually be encouraged to begin moving when safe and gradually resume eating and drinking. Your healthcare team will monitor urine output and bladder function, assess your incisions and provide guidance on wound care and activity before discharge.
Depending on the operation, a urinary catheter may remain temporarily while the bladder heals, or a ureteric stent may be used to maintain urine drainage while the ureter recovers. Recovery after limited excision can differ substantially from recovery following partial cystectomy or ureteric reconstruction, and follow-up will be arranged according to the procedure performed.
There is no single recovery period for urinary tract endometriosis surgery. Recovery depends on whether the procedure involves limited excision, partial cystectomy, ureterolysis or more extensive ureteric reconstruction, as well as the extent of endometriosis treated elsewhere in the pelvis.
The surgical approach, general health and any complications can also influence recovery. Returning to work and normal activities depends on the extent of surgery and the physical demands of your occupation, so activity should be increased gradually according to your surgeon's advice.
A urinary catheter and a ureteric stent perform different functions. A urinary catheter passes into the bladder to drain urine while the bladder recovers, whereas a ureteric stent is a thin internal tube placed within the ureter to maintain urine flow from the kidney to the bladder.
Either may be used temporarily depending on the surgery performed. For example, a catheter may be required after bladder repair, while a ureteric stent may be used following certain ureteric procedures. They are not necessary for every patient, and your surgeon will explain if either is expected as part of your treatment.
Surgery removes the urinary tract endometriosis identified and treated during the operation, but it does not guarantee a permanent cure. Endometriosis can persist or recur, and symptoms may return over time.
Ongoing management depends on the extent of disease, symptoms, reproductive plans and other areas of endometriosis. Follow-up may therefore include monitoring, medical treatment or, less commonly, further surgery where clinically necessary.
Pregnancy may remain possible after urinary tract endometriosis surgery because the reproductive organs are preserved where clinically possible. Surgery involving the bladder or ureters does not itself remove the uterus or ovaries.
However, fertility depends on factors beyond urinary tract involvement, including age, ovarian reserve, fallopian tube function and endometriosis affecting other reproductive structures. Surgery cannot guarantee pregnancy, and some women may require additional fertility treatment.
Ureter and bladder endometriosis occurs when endometriosis affects the urinary tract, with bladder disease involving the bladder wall and ureteric disease affecting the tubes that carry urine from the kidneys. Surgery may be considered for significant symptoms, deep bladder lesions or ureteric obstruction that interferes with urinary drainage or threatens kidney function.
Depending on the disease, treatment may range from bladder endometriosis excision or partial cystectomy to ureterolysis, ureteric reconstruction or reimplantation. Treatment is carefully planned according to the location and extent of disease, urinary tract function and involvement of other pelvic structures, with urological expertise incorporated where required.
Although surgery can remove disease, relieve symptoms and restore urinary drainage, endometriosis may persist or recur and outcomes vary between patients.
If you have been diagnosed with ureter or bladder endometriosis, consider scheduling a consultation with Dr Ma Li to discuss your condition, treatment options and the surgical approach most appropriate for your needs.
No. Bladder endometriosis involves endometriosis affecting the bladder, while a urinary tract infection is caused by infection within the urinary system. Some symptoms, such as painful or frequent urination, can overlap.
Yes. Significant ureteric narrowing can obstruct urine drainage from the kidney, causing hydronephrosis and potentially reducing kidney function if the obstruction persists.
Yes. Some patients have few or no urinary symptoms despite significant ureteric narrowing or obstruction, which is why appropriate urinary tract assessment can be important when ureteric disease is suspected.
No. The operation depends on the depth and location of disease. Partial cystectomy may be required for deep bladder wall involvement, but the appropriate procedure is determined individually.
A urologist may be involved when significant bladder or ureteric disease requires specialised urinary tract treatment or reconstruction. This is determined during pre-operative planning.
Operating time varies considerably according to the extent of endometriosis and whether bladder repair, ureterolysis or urinary tract reconstruction is required. Your surgeon can provide a more individual estimate after assessment.
Hospital stay depends on the procedure performed and your recovery. More extensive bladder or ureteric reconstruction may require a longer stay than limited minimally invasive excision.
This depends on the extent of surgery, your individual recovery and the physical demands of your work. Your surgical team will advise when it is appropriate to resume work and normal activities.












